
By DocMBS Billing Team · Last updated: October 2026
FQHC telehealth billing changed on October 1, 2026. For years, FQHCs and RHCs billed almost every Medicare distant-site telehealth visit on one code, G2025. That code is no longer used for those visits. If your team is still sending G2025 for October dates of service, those claims will come back.
This guide covers what replaced G2025, how to build an October claim, what Medicare pays, a worked example, and the denials to watch for.
Quick Answer
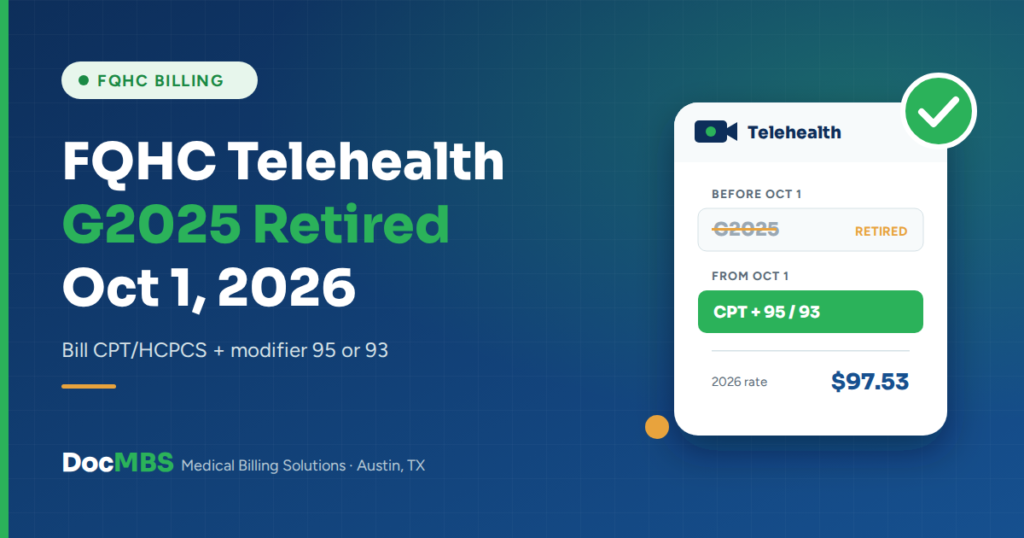
For dates of service on or after October 1, 2026, FQHCs and RHCs stop billing Medicare distant-site telehealth on G2025. Bill the actual CPT or HCPCS code for the service, with modifier 95 (video) or 93 (audio-only). Payment stays at one national rate: $97.53 for 2026. Source: CMS CR 14468.
Table of Contents
- What Changed for FQHC Telehealth Billing
- G2025 Before vs After October 1
- What Medicare Pays: $97.53 vs the $207.72 PPS Rate
- Mental Health Telehealth Is Different
- Step-by-Step: Billing an October Telehealth Claim
- Worked Example: One Telehealth Visit
- Common Denials and How to Fix Them
- What Stays the Same
- Texas Note
- Key Takeaways
- FAQs
- Sources
What Changed for FQHC Telehealth Billing
CMS issued Change Request (CR) 14468 on May 27, 2026 (MLN Matters MM14468). It says:
- Effective date: October 1, 2026 (dates of service on or after this date)
- Implementation date: October 5, 2026 (when Medicare contractors began applying it)
- Who it affects: FQHCs and RHCs billing Medicare for distant-site telehealth
- The change: bill the individual CPT or HCPCS code for the telehealth service instead of G2025
Why? With one code, Medicare could not see what service was actually provided. Code-level billing gives CMS that detail. It does not change what you are paid.
Watch Out: Some policy trackers online still say G2025 is used through December 31, 2026. That is out of date. CMS’s FQHC/RHC news page and CR 14468 both set October 1, 2026 as the switch date.
G2025 Before vs After October 1
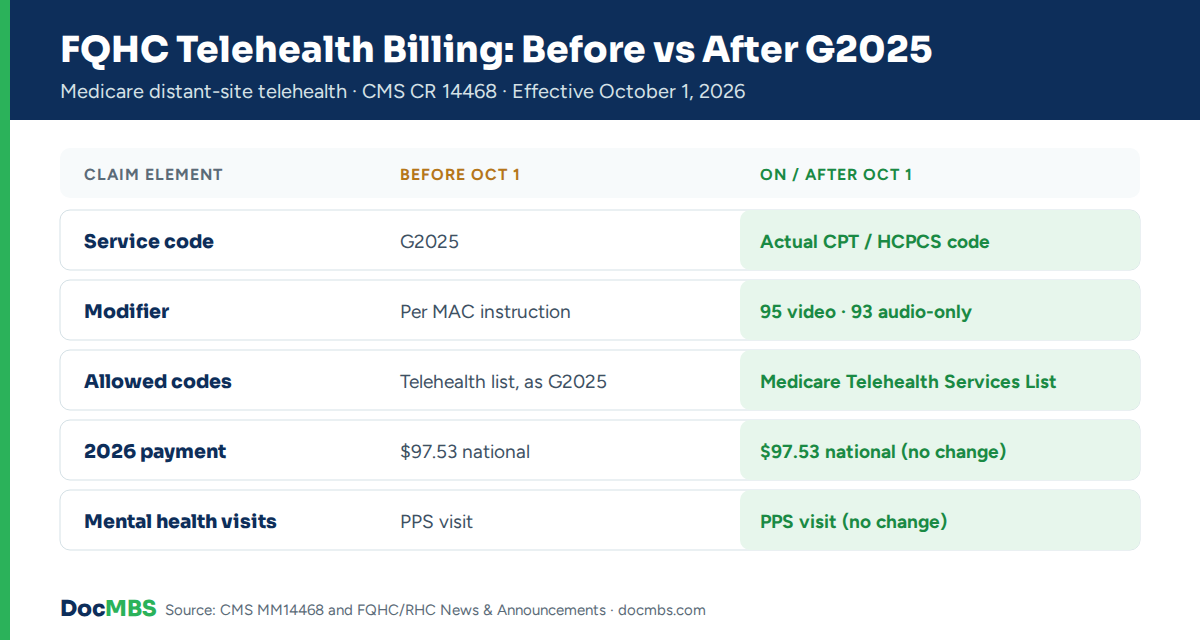
| Claim element | Before October 1, 2026 | On or after October 1, 2026 |
|---|---|---|
| Service code | G2025 for almost every distant-site telehealth service | The actual CPT or HCPCS code (for example, 99213) |
| Modifier | Varied by MAC instruction | 95 for audio-video, 93 for audio-only |
| Which codes are allowed | Services on the Medicare telehealth list, reported as G2025 | Codes on the Medicare Telehealth Services List |
| Revenue code | G2025 was reported on a 052X line | “The appropriate revenue code,” per CR 14468 and your MAC’s instructions |
| Payment | National telehealth rate ($97.53 in 2026) | Same national rate ($97.53 in 2026) |
| Mental health visits | Billed as FQHC mental health visits | No change (see below) |
Sources: CMS MM14468 (CR 14468) and CMS FQHC/RHC News & Announcements.
What Medicare Pays: $97.53 vs the $207.72 PPS Rate
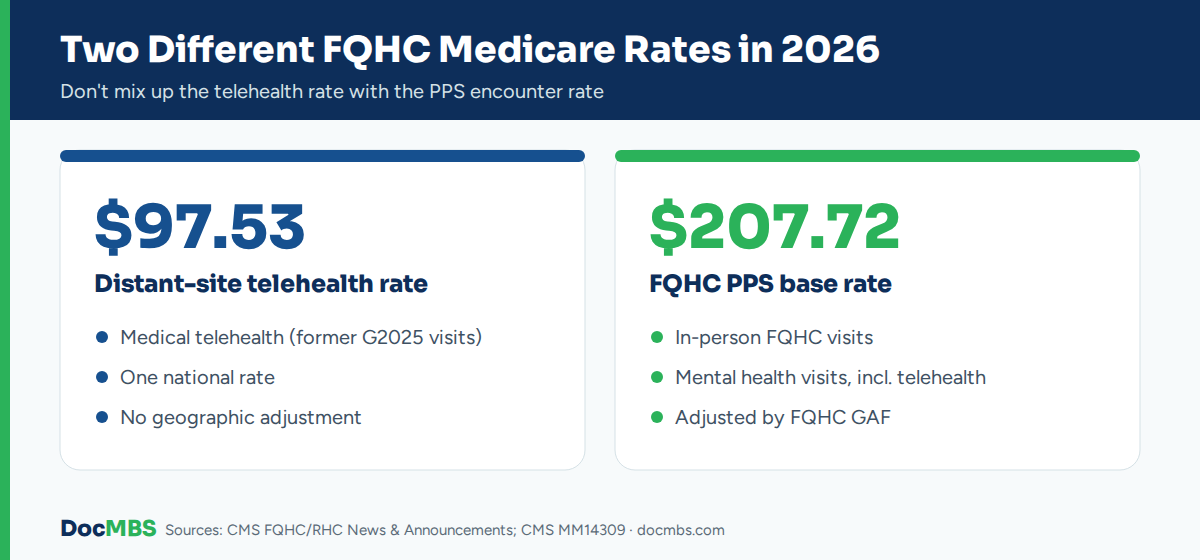
This is where many billing teams get confused. FQHCs have two very different Medicare rates in 2026:
| Rate | 2026 amount | Used for | Adjusted by location? |
|---|---|---|---|
| Distant-site telehealth rate | $97.53 | Medical telehealth services (the visits that used to be G2025) | No, one national rate |
| FQHC PPS base rate | $207.72 | In-person FQHC visits, and mental health visits including by telehealth | Yes, by the FQHC geographic adjustment factor |
Sources: CMS FQHC/RHC News & Announcements ($97.53); CMS MM14309 ($207.72, up 2.5% from $202.65 in 2025).
The telehealth rate is based on the average Medicare Physician Fee Schedule amount for services on the telehealth list. It is not the PPS encounter rate, and the new code-level billing does not change that. A medical telehealth visit pays $97.53 whether you bill 99212 or 99215.
October telehealth claims coming back?
DocMBS fixes FQHC claims rejected for G2025, missing modifiers or the wrong code, and updates your charge master so it doesn’t happen again. FQHC billing is one of our core specialties.
Mental Health Telehealth Is Different
CR 14468 is about non-behavioral health telehealth. Mental health visits delivered by telehealth are handled differently:
- Since 2022, Medicare counts an FQHC mental health visit by real-time telecommunication as an FQHC visit. It is paid under the PPS, not the $97.53 telehealth rate.
- Keep billing these visits the way you did before October 1: the FQHC mental health payment code with the qualifying service, on the mental health revenue line (0900), with the telehealth modifier your MAC requires.
- CMS also added optional add-on codes G0568, G0569 and G0570 for behavioral health integration and psychiatric collaborative care in 2026. G0512, G0071 and G0511 are no longer reportable.
Pro Tip: Mental health telehealth pays the full PPS rate, so getting it right matters. On the FQHC claims we review, the costly mistake is the reverse of the G2025 problem: a mental health visit billed as a $97.53 medical telehealth service.
Step-by-Step: Billing an October Telehealth Claim
- Check the date of service. On or after October 1, 2026 uses the new method. Earlier dates keep the old one.
- Decide if it’s a mental health visit. If yes, bill it as an FQHC mental health visit under PPS. If not, keep going.
- Pick the CPT or HCPCS code that describes the service, such as an office/outpatient E/M code.
- Confirm the code is on the Medicare Telehealth Services List for 2026.
- Add the modifier: 95 for real-time audio and video, 93 for audio-only.
- Use the revenue code your MAC instructs. CR 14468 says “the appropriate revenue code” and leaves the value to contractor guidance. Check your MAC’s FQHC billing page.
- Remove G2025 from your charge master and claim templates for October dates.
- Bill, then check the first remits. Expect $97.53 less coinsurance. Anything else needs a closer look.
Worked Example: One Telehealth Visit
Example only. On October 14, 2026, an FQHC nurse practitioner sees an established Medicare patient by video for diabetes follow-up. The FQHC’s charge is $150.
| Item | Before October 1 | October 14, 2026 |
|---|---|---|
| Code billed | G2025 | 99213-95 (example code) |
| Medicare payment rate | $97.53 | $97.53 |
| Coinsurance (20% of the lower of the rate or the charge) | $19.51 | $19.51 |
| Medicare pays | $78.02 | $78.02 |
How the math works: the rate ($97.53) is lower than the charge ($150), so coinsurance is based on the rate: $97.53 × 20% = $19.51. Medicare pays the rest, $78.02, before any sequestration reduction. If the charge had been lower than $97.53, coinsurance would be based on the charge instead. The Part B deductible does not apply to FQHC services.
The payment is the same. Only the coding changed, but billing G2025 for this visit would now get the claim returned.
Common Denials and How to Fix Them
| Problem | What you may see | How to fix it |
|---|---|---|
| G2025 billed for an October 1 or later date of service | Claim returned to provider or denied (CO-16 or CO-181) | Replace G2025 with the actual CPT/HCPCS code and modifier, then resubmit |
| No telehealth modifier on the line | CO-4 (modifier missing or inconsistent) | Add 95 (video) or 93 (audio-only) |
| Code not on the Medicare telehealth list | CO-96 (non-covered) or a return | Check the 2026 telehealth list; the service may need to be in person |
| Wrong revenue code for the telehealth line | Return to provider (CO-16) | Use the revenue code your MAC’s instructions require |
| Mental health visit billed as medical telehealth | Paid $97.53 instead of the PPS rate | Cancel and rebill as an FQHC mental health visit |
| Audio-only service billed with 95 | Audit risk or denial | Use 93 for audio-only, and document why video wasn’t used |
If October claims are piling up in your return queue, our FQHC billing and denial management services can clear them and fix the setup behind them.
What Stays the Same
- Telehealth is still allowed. The Consolidated Appropriations Act, 2026 extends FQHC and RHC distant-site telehealth until January 1, 2028.
- The in-person rule is still on hold. CMS says the requirement for an in-person mental health visit before telehealth mental health services will not take effect until after January 1, 2028.
- Your practitioners can work from anywhere while working for the FQHC, within their scope.
- The payment rate is the same: $97.53 for 2026, updated each year.
- Direct supervision by real-time video (not audio-only) is now permanent under the 2026 Physician Fee Schedule rule.
Texas Note
CR 14468 is a Medicare rule. It does not change how Texas Medicaid or Medicaid managed care plans pay FQHCs for telehealth. Texas Medicaid has its own FQHC encounter rules and telehealth policies, published by TMHP in the Texas Medicaid Provider Procedures Manual. Keep separate billing rules for Medicare and Texas Medicaid claims, and check with each Medicaid MCO before changing anything on their claims.
Key Takeaways
- From October 1, 2026, FQHCs and RHCs bill Medicare telehealth with the actual CPT/HCPCS code, not G2025.
- Add modifier 95 for video or 93 for audio-only.
- Payment is still $97.53 for 2026, one national rate. It is not the $207.72 PPS rate.
- Mental health telehealth visits keep their PPS billing and are not part of this change.
- Telehealth flexibilities for FQHCs run until January 1, 2028.
FAQs
Is G2025 discontinued for FQHCs?
For Medicare distant-site telehealth with dates of service on or after October 1, 2026, yes. CMS CR 14468 tells FQHCs and RHCs to bill the individual CPT or HCPCS code for the service instead of G2025. Claims for dates of service before October 1 are billed the old way.
What do FQHCs bill instead of G2025?
They bill the CPT or HCPCS code that describes the telehealth service, as long as it is on the Medicare Telehealth Services List. Add modifier 95 for real-time audio and video, or modifier 93 for audio-only. Use the revenue code your Medicare Administrative Contractor instructs.
How much does Medicare pay FQHCs for telehealth in 2026?
Medicare pays FQHCs and RHCs a single national rate of $97.53 for distant-site telehealth in 2026. It is not adjusted for location and is not the PPS rate. The patient’s coinsurance is 20% of the lower of the rate or the FQHC’s charge.
Does the G2025 change affect mental health telehealth?
No. CR 14468 covers non-behavioral health telehealth. Mental health visits furnished by telehealth are still FQHC visits paid under the PPS. Keep billing them the way you did before October 1, with the telehealth modifier your MAC requires.
What modifier do FQHCs use for telehealth after October 1, 2026?
Use modifier 95 when the service is delivered by real-time audio and video. Use modifier 93 when it is delivered by telephone or another real-time audio-only system. Make sure your documentation shows which method was used.
How long can FQHCs keep billing Medicare telehealth?
The Consolidated Appropriations Act, 2026 extends FQHC and RHC distant-site telehealth until January 1, 2028. CMS also says the in-person requirement for mental health telehealth will not take effect until after January 1, 2028.
Update Your FQHC Telehealth Billing Now
The new FQHC telehealth billing rule is simple once it’s set up: drop G2025, bill the real code, add 95 or 93, and keep mental health visits on PPS. The payment doesn’t change, but the claims that miss the switch will sit in your return queue.
DocMBS bills for FQHCs every day. Book a free FQHC billing review and we’ll check your October telehealth claims and charge master against CR 14468.
Sources
- CMS: MLN Matters MM14468 (CR 14468): RHCs and FQHCs Billing Distant Site Telehealth, May 27, 2026
- CMS: FQHC/RHC News & Announcements
- CMS: MLN Matters MM14309: FQHC PPS rate CY 2026
- CMS: Medicare Telehealth Services List
Last updated: October 2026. This article is for education only. Confirm revenue codes and claim details with your Medicare Administrative Contractor before billing.
Talk to our billing team
Book an appointment and discuss your practice's billing with a DocMBS specialist.